
Christoff
Community trophies


Game trophies


Posts
38
I Am Angry
I am angry that uncertainty became certainty, that softened language obscures what is actually being claimed, that scepticism is treated as hostility, and that while we argue about FND, my wife keeps getting sicker.
When the Tests Find Something, but We Still Have to Find the Answers
An update on my wife’s worsening gastrointestinal problems, the objectively demonstrated delayed intestinal transit, what has been excluded, what still needs investigation, and why it feels wrong that we are being left to work out the next steps ourselves.

Open Letter to Zachary Grin, DPT
An open letter addressing the removal of a disputed cartoon, clarifying what was—and was not—claimed, and reaffirming FND Nope’s commitment to open and critical discussion of the FND framework.
The Common Phenotypes Hypothesis
An exploration of FND, positive rule-in signs, comorbidity, predictive processing, diagnostic closure, and whether functional symptoms may reflect common phenotypes arising from multiple underlying conditions.

The Belief Prerequisite: How FND Treatment Echoes Faith Healing
One of the most striking things you notice when you first start reading the literature on FND is how crucial it is considered for patients to accept and believe in the diagnosis. Without that belief, treatment is often regarded as futile. They simply will not get better.

What Makes a Doctor a Good Doctor?
A reflection on what makes a good doctor in the context of complex chronic illness, focusing on collaboration, systems thinking, and clinical humility.
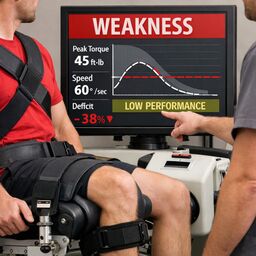
Fatigable Weakness vs Functional Weakness: Why Hoover’s Sign Can Mislead When Isokinetic Testing Shows Otherwise
Examines Hoover's sign in a patient with true fatigable weakness. Highlights how objective isokinetic testing better captures performance deficits than traditional clinical signs, preventing misinterpretation as functional weakness.

When Diagnosis Becomes Doctrine: Questioning FND and Clinical Authority
When I started this website in July 2025, I received a lot of pushback from FND proponents. Some felt that the website was highly offensive and disrespectful, and urged me to please take the website down, which I obviously did not do.

FND's Flawed Analogy: When 'Software' Problems can Hide Undetected Hardware Damage
One of the most common analogies that you would come across within FND literature is the software/hardware analogy.

If FND Scepticism Feels Like a Personal Attack, It Might Be Time for Introspection
FND patient communities provide support but risk echo chambers: illness becomes identity, criticism feels like attack, closing doors to misdiagnosis & recovery—modern hysteria protected by groupthink.
Comments
53LOL, I love this quote
‘That’s good that it’s all in your head, because that’s where your brain is.’
Since you mentioned that you are a nurse, I would also be very interested in your perspective on a post I wrote: When Nursing Education Reinforces a Diagnosis.
It looks at an Australian FND nursing education guide that explicitly encourages nurses to reinforce the diagnosis and discusses patient scepticism, pursuit of alternative diagnoses and further investigation largely as barriers to recovery. My concern is that it gives considerably less attention to diagnostic uncertainty, reassessment, or recognising when new symptoms or progression might justify questioning the original diagnosis.
Given your nursing background, I would genuinely be interested to know how you view that kind of educational approach, particularly whether you think reinforcing the diagnosis is an appropriate role for nurses, and how that should be balanced against remaining alert to changes that might warrant reassessment.
As you have done with letters posted to you (for public record), here is the one I received.
To FNDNope,
I am absolutely furious about what you are doing.
You present yourselves as a platform for scepticism and critical discussion around Functional Neurological Disorder, but from where I am standing, what you are actually doing is undermining confidence in doctors, amplifying anecdotes, questioning established medical consensus, and encouraging people to believe that their FND diagnoses may be wrong.
Do you understand how fucking dangerous that can be?
Doctors spend years training to diagnose neurological disorders. FND is a recognised diagnosis with established clinical signs and an extensive scientific literature behind it. Yet your website seems determined to focus on every case where somebody was misdiagnosed, every limitation in the evidence, and every uncomfortable question about diagnostic accuracy.
Patients need reassurance, not endless scepticism. They need to accept their diagnoses and engage with treatment, not be encouraged to interrogate every assumption their clinicians make.
And frankly, the cartoons and satire make it worse. Medicine is serious. FND is serious. Turning disagreements about diagnosis into jokes about doctors, diagnostic overshadowing, and "Must be the FND" may be amusing to you, but it risks portraying clinicians as arrogant or intellectually closed simply because they are following accepted medical practice.
What makes this even more troubling is the constant cosplaying as a clinician while simultaneously claiming to be merely a sceptic asking questions. You cannot spend your time adopting the posture and authority of a medical professional, making sweeping pronouncements about diagnoses and clinicians, and then retreat behind "it's just satire" or "I'm just asking questions" whenever challenged. You do not get to have it both ways.
You also seem obsessed with the possibility that FND can distract clinicians from alternative diagnoses. Of course doctors can make mistakes. Nobody denies that. But continually highlighting those mistakes creates a completely distorted picture of ordinary clinical practice.
There comes a point where "scepticism" stops being healthy questioning and starts undermining trust.
And if you think operating from another country puts you safely beyond accountability, think again.
The internet is not some magical jurisdiction free zone. Operators can be identified through lawful processes, records can be preserved, and legal advice can be obtained across borders. If what you are publishing crosses the legal line, then every available lawful avenue can be explored to identify the responsible parties and pursue the matter in the appropriate jurisdiction.
Do not assume that geographical distance means nobody can reach you legally. It doesn't.
Keep the screenshots. Keep the archives. Keep laughing. If this crosses the threshold for legal action, those records may eventually become evidence.
Perhaps instead of constantly asking what the FND literature gets wrong, you should start asking yourself whether you're prepared to defend what you publish when somebody finally decides to challenge it properly.
This website is irresponsible, provocative, and deeply frustrating.
Consider this a warning. If you continue crossing the line, legal action may only be the beginning of the consequences you have to deal with. There are other entirely legitimate avenues available, and I suggest you think very carefully before assuming that distance, anonymity, or international borders place you beyond accountability. If necessary, the people responsible can be identified through lawful means. Keep pushing this and you may find this becomes considerably uglier than a dispute between strangers on the internet, this will make the Röhm-Putsch look like a walk in the park.
You chose to post a lengthy response on my website, address me directly, question my honesty, and then instruct me not to respond. You do not get to enter my space, make allegations about me, and then declare that only your account may remain on the record.
I never stated that the character was you. I acknowledge the resemblance, but depicting you was not my intention. A laughing emoji is not an admission of identity. Nevertheless, you objected, and I removed the image to de-escalate the dispute, not to concede the allegations you subsequently attached to it.
There is also a recurring problem with your response: several of the points you hammer on were already addressed in the very letter you were responding to.
I have occasionally used "MS" where CIS suggestive of MS was more precise. However, I have repeatedly made that distinction clear, including in the very letter you were responding to. Treating occasional imprecision as dishonesty while ignoring that clarification is unfair.
Likewise, I have never claimed to know how you personally practise inside your clinic. My criticism concerns arguments and attitudes expressed publicly, not clinical encounters to which I have no access. Your explanation of your own assessment and referral procedures is now on the record, and I accept it as your account of your practice.
When points already conceded, qualified, or explicitly addressed in the original letter are presented back to me as evidence of dishonesty, it leaves me wondering whether you actually read the letter in full before responding to it.
Your comments on my wife are a different matter.
You argue that you are entitled to an opinion because I placed information about her medical workup online. Of course you are entitled to an opinion. But despite your lengthy response and extensive recital of your credentials, you provide no clinical reasoning about her case. You identify no examination findings supporting your position, address no progression or subsequent findings, and offer no meaningful differential diagnosis.
You have never examined her.
Reading information posted online does not give you a complete clinical understanding of a woman with a complex and evolving medical history. Yet you speak with a degree of confidence that the information available to you simply does not justify.
Your credentials may establish experience with FND. They do not give you access to investigations you have not seen, examinations you did not perform, follow-up information you do not possess, or the longitudinal evolution of her condition. Credentials are not evidence, and confidence is not clinical reasoning.
I will correct demonstrable errors. I will distinguish fact from inference. I will revise my position when evidence warrants it.
What I will not do is stop examining FND, diagnostic closure, or documented cases of misdiagnosis because clinicians object to being challenged.
More fundamentally, I believe FND itself rests on a very low epistemic bar. Considerable diagnostic certainty can be built upon clinical signs whose mechanisms, interpretation, and specificity are not equivalent to establishing a known underlying disease process, within a diagnostic framework that continues to evolve.
In my wife’s case, even that already low bar was not demonstrably met.
That is the substantive criticism.
Your response does not answer it. Repeating points that the original letter already acknowledged does not answer it either. It substitutes credentials, indignation, and allegations about my honesty and motives for an evidence-based response to the argument I am actually making.
I am not sure whether this website will prove helpful to someone someday. I do know that this conversation is not helping anyone at this stage.
I had hoped this would be more than mudslinging. I guess not. Closing this thread.
Theoretically, we have freedom of speech on this side of the world too 😄 Although I'm not entirely convinced my country would go out of its way to defend me, they'd probably throw me under the bus if given half a chance, hehe.
But there will be other battles worth fighting. For my part, I'm going to try to keep things clean and civil and focus on the actual issues rather than personalities.
I am, however, learning a great deal about the kind of discourse I'm dealing with here. At times it feels almost Trumpian in nature: disagreement quickly becomes outrage, criticism becomes an attack, and then everything escalates from there.
I'd rather stick to the substance.
You’re right that this argument is applied unevenly mostly to conditions historically called psychogenic and mainly affecting women.
I was surprised when I first delved into the literature how nebulous things were not at all like the hard sciences we are used to. Medicine balances known evidence against unknowns with practical judgment and philosophy under uncertainty. That is why the tension exists. And given from what I've seen I am not sure that some clinicians even realise that this tension exists. You've got clinicians treating this as a hard science while the underlying evidence is not that at all that is what we are kicking against. And patients expecting this to be treated as a hard science when none of it is its all a bit disconnected. The limit on testing is real but using it selectively while other idiopathic diseases simply stay unknown cause no psych referral is the double standard.
This is exactly where something like FND can fail horribly when these unknowns are treated as knowns.
Thank you for sharing. This might help someone in the future. FND is the modern descendant of hysteria, so it is hardly surprising that the same diagnostic overshadowing persists. Ménière’s was one of the physical diseases whose symptoms could historically disappear into the broad category of “hysteria.” Today, vertigo can similarly be labelled as functional or PPPD before an evolving inner-ear disorder has been adequately investigated.
I’m glad you trusted your instincts and found a specialist who looked further. It is concerning that FND was suggested while a physical explanation remained unresolved, especially since your symptoms disappeared after vestibular nerve section. If you don’t mind sharing, how long have you been symptom-free since the surgery?
What always boggles my mind is how quickly skepticism about the FND label, especially in cases like this one, gets framed as denial or something harmful. Skepticism is not denial of the symptoms or the suffering. It is a legitimate response when the patient themselves says they don't understand how the diagnosis was reached, no clear positive clinical signs or explanation were communicated, and it felt like a nothing else fits conclusion, with no real treatment plan or forward path.
Shouldn't the priority be listening to the patient's actual experience and asking why the diagnostic process wasn't more transparent? Good medicine welcomes questions and second opinions, especially with sudden, purely cognitive changes that have devastated someone's career and daily life.
Why discourage exploring reasonable alternatives such as Long COVID related brain fog, POTS, autoimmune encephalitis, microbiome issues, and so on? Considering differentials doesn't invalidate FND if that is the right fit. It just protects the patient from a potentially premature label. Many of us have seen cases where digging deeper changed everything.
Discussions started
3Initial interview with Christine Aumann, Maddie Aumann’s mother, on REAL TALK 93.3FM, discussing Maddie’s Functional Neurological Disorder (FND) diagnosis, her subsequent medical journey, and the impact the FND diagnosis had on her care.
From https://www.facebook.com/RealTalk933fm/videos/1095299976492411/
You can literally go onto https://fndconnect.org.uk/shop/product/fnd-connect-i-have-seizures-lanyard-and-card
And for £ 4.99 you can buy yourself a lanyard to inform bystanders to effectively discourage appropriate emergency care.
Someone may assume every episode is "just another functional seizure." But seizures can change, suffer a head injury, have a stroke,
low blood sugar, cardiac syncope, or another medical emergency.

Looking back, was there a symptom(s) that should have prompted doctors to investigate further before diagnosis FND?
Similar case shared on the FB Group
https://www.facebook.com/groups/1551839625936156/permalink/1741915683595215/